Table of Contents
Abstract
The concept of healthy aging extends far beyond the mere absence of disease; it encompasses a proactive, multidimensional lifestyle that integrates physical activity, cognitive stimulation, social participation, and stress management. As global demographics shift toward older populations, particularly in rapidly aging nations like China, the need to accurately quantify these lifestyle behaviors has become paramount. The healthy aging Activity Engagement Scale (HAAE) was originally developed to capture this holistic view of aging, moving away from fragmented assessments that only look at single domains like diet or exercise.
This specific research focuses on the cross-cultural adaptation and psychometric validation of the HAAE for use among middle-aged and Older adults in mainland China. By translating this instrument, researchers aimed to provide a robust, culturally sensitive tool capable of evaluating how actively individuals are participating in behaviors known to mitigate chronic illness and cognitive decline. The availability of such a validated measure is crucial for public health initiatives, allowing practitioners to establish baselines, track lifestyle interventions, and promote Preventative Health strategies long before the onset of severe age-related conditions.
📊 Psychometric Scorecard
32
Multidimensional
0.97
0.982
📍 China
Authors
Purpose
Historically, clinical assessments of Older adults have relied on disparate questionnaires that isolate specific health behaviors, such as physical activity trackers or dietary logs. This fragmented approach fails to capture the synergistic nature of a truly healthy lifestyle. The primary purpose of validating the Chinese version of the HAAE is to bridge this methodological gap by offering a unified, comprehensive instrument that evaluates multiple facets of healthy aging simultaneously.
For researchers and clinicians, this scale serves as a vital preventative tool. By applying it not just to the elderly, but also to middle-aged populations, healthcare providers can identify lifestyle deficits early on. This early detection is critical for implementing targeted interventions that encourage cognitive engagement, social interaction, and physical exercise, ultimately reducing the future burden of chronic diseases and enhancing the overall quality of life in later years.
Construct
The psychological and behavioral construct measured by the HAAE is multidimensional healthy aging engagement. Theoretically, this construct is rooted in the biopsychosocial model of health, which posits that successful aging is not merely a biological process but is heavily influenced by psychological resilience, cognitive maintenance, and social connectivity. The scale operationalizes this by evaluating how frequently and intensely individuals participate in activities known to foster these domains.
The instrument captures three primary underlying factors, reflecting a holistic lifestyle approach. These dimensions encompass physical health behaviors, cognitive and social enrichment, and psychological well-being. Together, these interconnected domains provide a comprehensive profile of an individual's proactive engagement in their own aging process, aligning with contemporary gerontological theories that emphasize active, rather than passive, aging.
Validity
Establishing the validity of a translated psychometric tool is essential to ensure it measures what it intends to measure within a new cultural context. In this validation study, the researchers rigorously evaluated both content and structural validity. Content validity was confirmed through expert consultation, yielding an exceptionally high Scale-Level Content Validity Index of 0.969, indicating that the translated items were highly relevant and culturally appropriate for a Chinese demographic.
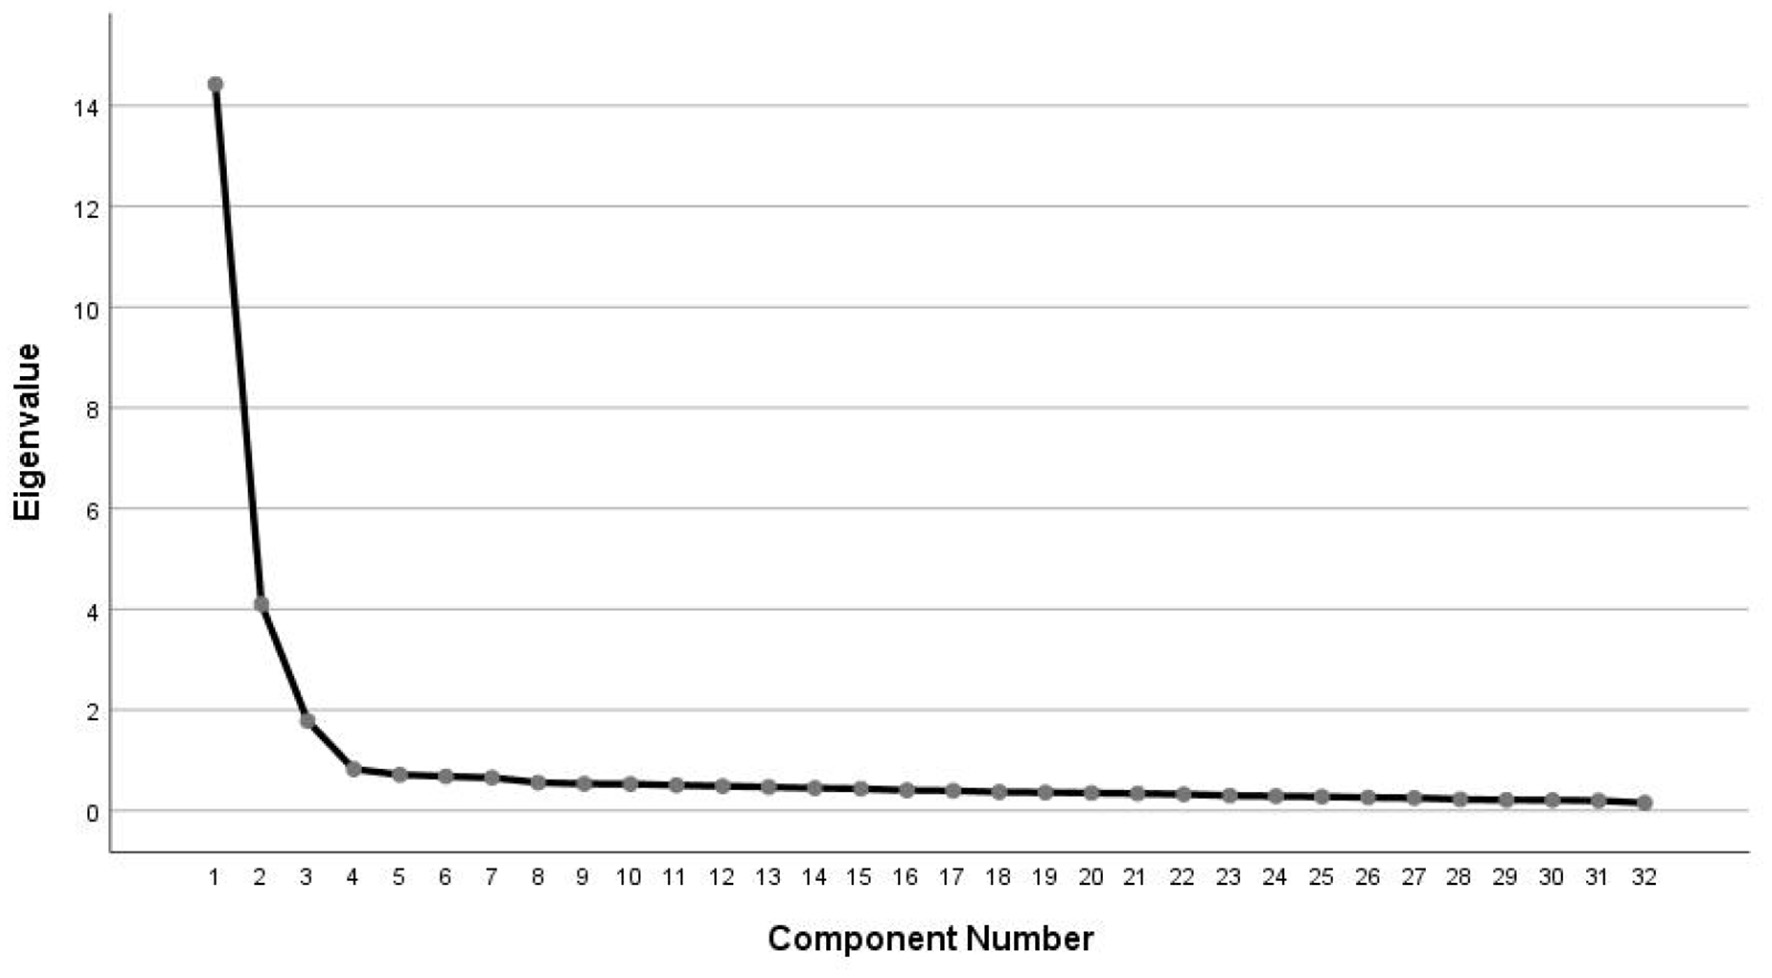
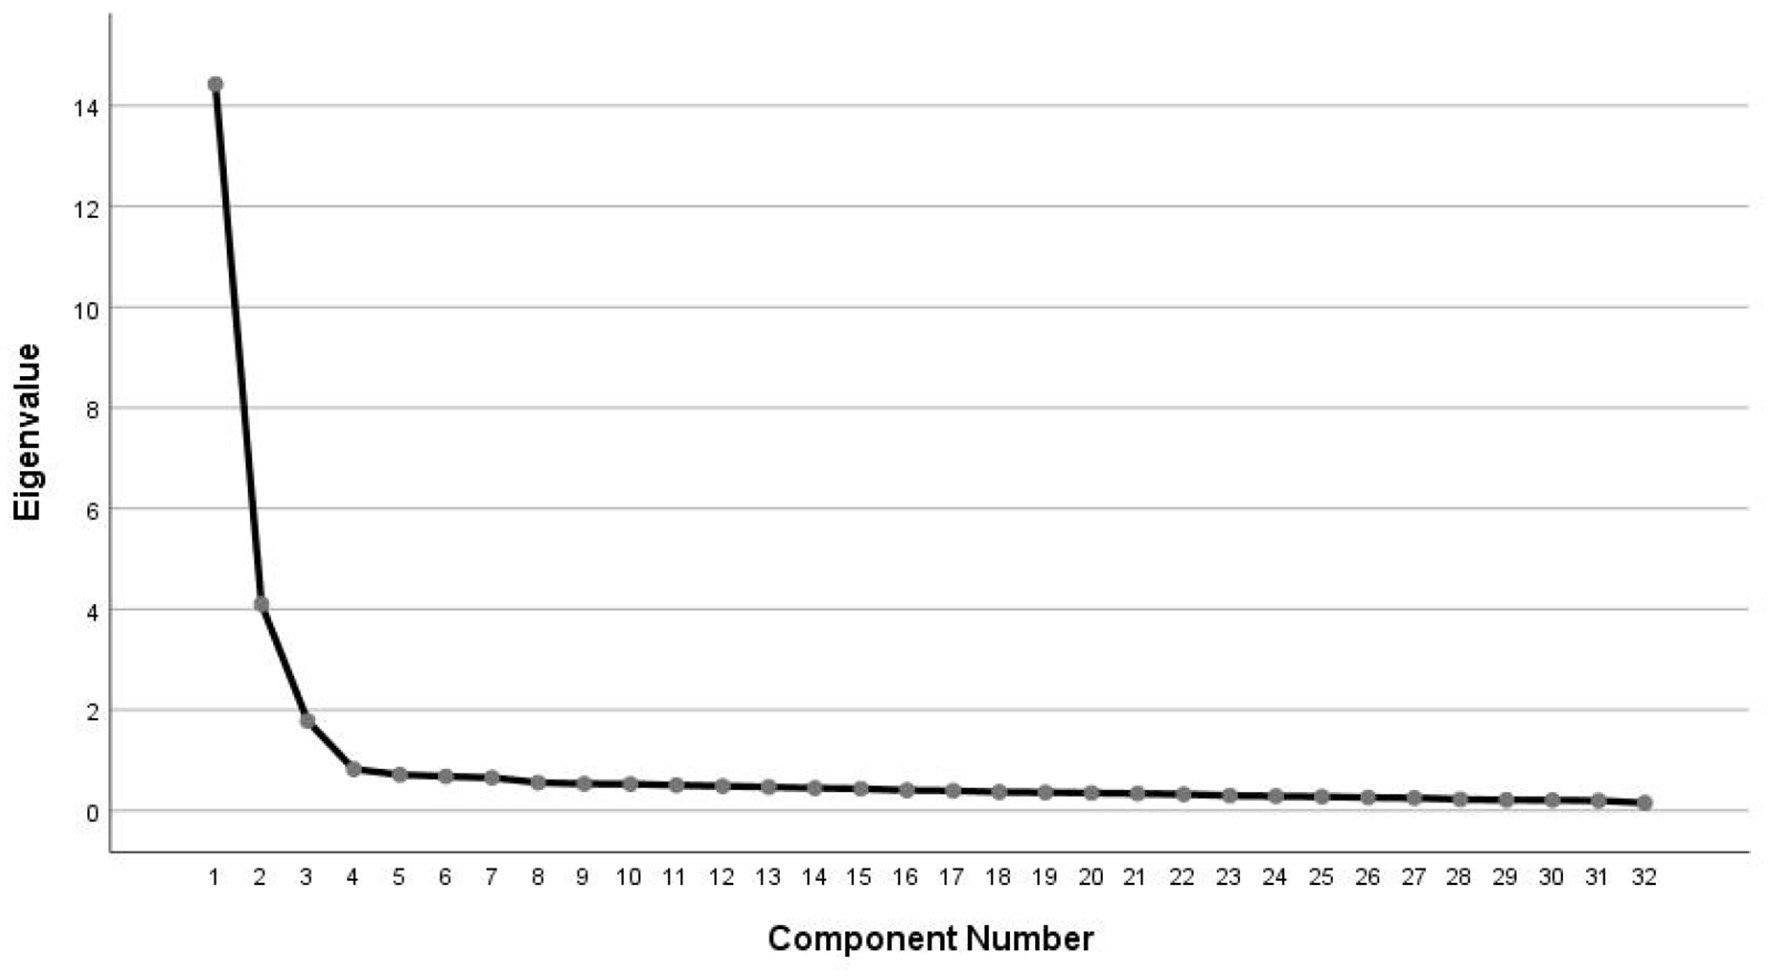
To examine the underlying structure, the research team employed both Exploratory Factor Analysis and Confirmatory Factor Analysis. The exploratory phase successfully extracted a three-factor model that aligned with the original English version. Subsequent confirmatory analysis demonstrated an excellent fit for this structure. Fit indices such as the Comparative Fit Index at 0.982 and Tucker-Lewis Index at 0.981 were well above standard thresholds, and the Root Mean Square Error of Approximation was notably low at 0.030, indicating that the theoretical model perfectly matched the observed data.
Reliability
Reliability in psychometrics refers to the consistency and stability of a measurement tool. The Chinese adaptation of the HAAE demonstrated outstanding internal consistency, with an overall Cronbach's alpha coefficient of 0.965. This exceeds standard psychometric benchmarks, indicating that the 32 items work together cohesively to measure the overarching construct of healthy aging engagement. The individual sub-dimensions also showed strong internal reliability, with alpha values ranging from 0.898 to 0.957, ensuring that each specific behavioral domain is measured accurately.
Beyond internal consistency, the researchers also established the temporal stability of the scale through test-retest reliability over a two-week interval. The resulting correlation coefficient of 0.850 was highly satisfactory, proving that the scale yields consistent results over time when an individual's lifestyle habits remain unchanged. Additionally, a strong split-half reliability of 0.807 further corroborated the instrument's robust internal structure, making it a highly dependable tool for both cross-sectional and longitudinal research.
Factor Analysis
The structural integrity of the translated scale was rigorously tested using a dual-phase factor analytic approach. Initially, Exploratory Factor Analysis was utilized to uncover the natural grouping of the 32 items within the new cultural sample. This analysis revealed three distinct common factors, which collectively accounted for 63.448% of the total variance. Importantly, every item demonstrated a strong factor loading greater than 0.4, confirming that no items needed to be discarded due to poor conceptual alignment.
Following the exploratory phase, Confirmatory Factor Analysis was applied to mathematically verify this three-factor model. The results were highly supportive of the proposed structure. The chi-square to degrees of freedom ratio was 1.393, well below the conservative threshold of 3.0. Other key metrics, including a Goodness-of-Fit Index of 0.911, indicated an exceptional model fit. These findings provide strong empirical evidence that the three-dimensional structure of the HAAE is robust and culturally invariant.
Subscales
| Subscale | Items | Description |
|---|---|---|
| Factor 1 | One of three common factors extracted representing a dimension of healthy aging engagement. | |
| Factor 2 | One of three common factors extracted representing a dimension of healthy aging engagement. | |
| Factor 3 | One of three common factors extracted representing a dimension of healthy aging engagement. |
Instrument
| Test Type | Self-report questionnaire |
| Format | 32 items |
| Language | Chinese |
| Population | Adults, Older adults |
| Age Group | 45 years and older |
| Administration | Self-administered |
Figures


Healthy Aging Activity Engagement Scale Items
Items are currently not available
The individual items of this scale are not publicly available. Researchers interested in using this instrument should contact the original authors directly to request the scale materials.
Sample
A total of 424 middle-aged and elderly individuals (aged 45 and older) were recruited via convenience sampling from communities in Jiangsu, Liaoning, Shandong, and Heilongjiang provinces in China. The sample consisted of 48.3% females and 51.7% males, with 62.7% of participants aged 60 and above.
Cite This Paper
Tingting Lu, Linghui Kong, Huijun Zhang (2022). healthy aging Activity Engagement Scale. Frontiers in public health. https://doi.org/10.3389/fpubh.2022.986666
References
28 references
- (2021). Bulletin of the Seventh National Population Census–Basic Information on the Work of the Seventh National Population Census.,
- Abe (2012). Total daily physical activity and the risk of AD and cognitive decline in Older adults. Neurology, 79 1071. 🔗 https://doi.org/10.1212/WNL.0b013e31826bd5cf
- Osborne (2020). Disentangling the links between psychosocial stress and cardiovascular disease. Circ Cardiovasc Imaging., 13 e010931. 🔗 https://doi.org/10.1161/CIRCIMAGING.120.010931
- Kivimäki (2018). Effects of stress on the development and progression of cardiovascular disease. Nat Rev Cardiol., 15 215. 🔗 https://doi.org/10.1038/nrcardio.2017.189
- Malhotra (2017). Saturated fat does not clog the arteries: coronary heart disease is a chronic inflammatory condition, the risk of which can be effectively reduced from healthy lifestyle interventions. Br J Sports Med., 51 1111. 🔗 https://doi.org/10.1136/bjsports-2016-097285
- Kushi (2012). American cancer society guidelines on nutrition and physical activity for cancer prevention: reducing the risk of cancer with healthy food choices and physical activity. CA Cancer J Clin, 62 30. 🔗 https://doi.org/10.3322/caac.20140
- Fitzpatrick (2009). Mid- and late-life obesity: risk of dementia in the cardiovascular health cognition study. Arch Neurol, 66 336. 🔗 https://doi.org/10.1001/archneurol.2008.582
- Anstey (2011). Body mass index in midlife and late-life as a risk factor for dementia: a meta-analysis of prospective studies. Obes Rev., 12 e426. 🔗 https://doi.org/10.1111/j.1467-789X.2010.00825.x
- Yano1 (2016). Isolated systolic hypertension in y oung and middle-aged Adults. Curr Hypertens Rep., 18 78. 🔗 https://doi.org/10.1007/s11906-016-0686-x
- De la Rosa (2020). Physical exercise in the prevention and treatment of Alzheimer's disease. J Sport Health Sci, 9 394. 🔗 https://doi.org/10.1016/j.jshs.2020.01.004
- Beeri (2012). Being physically active may protect the brain from Alzheimer disease. Neurology., 78 1290. 🔗 https://doi.org/10.1212/WNL.0b013e3182535f0e
- Steptoe (2019). Leading a meaningful life at older ages and its relationship with social engagement, prosperity, health, biology, and time use. Proc Natl Acad Sci U S A., 116 1207. 🔗 https://doi.org/10.1073/pnas.1814723116
- Wang (2021). Social engagement and physical frailty in later life: does marital status matter?. BMC Geriatr., 21 248. 🔗 https://doi.org/10.1186/s12877-021-02194-x
- Popovic (2022). Defining the importance of stress reduction in managing cardiovascular disease – the role of exercise. Prog Cardiovasc Dis., 70 84. 🔗 https://doi.org/10.1016/j.pcad.2022.01.008
- Wirtz (2017). Psychological stress, inflammation, and coronary heart disease. Curr Cardiol Rep., 19 111. 🔗 https://doi.org/10.1007/s11886-017-0919-x
- Katsarou (2013). Perceived stress and vascular disease: where are we now?. Angiology., 64 529. 🔗 https://doi.org/10.1177/0003319712458963
- Natelson (2004). Stress, hormones and disease. Physiol Behav., 82 139. 🔗 https://doi.org/10.1016/j.physbeh.2004.04.038
- Schmitter-Edgecombe (2019). Development and psychometric properties of the healthy aging Activity Engagement Scale (HAAE). Aging Ment Health., 23 357. 🔗 https://doi.org/10.1080/13607863.2017.1414147
- Sim (2022). Sample size requirements for simple and complex mediation models. Educ Psychol Meas., 82 76. 🔗 https://doi.org/10.1177/00131644211003261
- Brislin (1980). Translation and Content Analysis of Oral and Written Material. 389.
- Bruton (2000). Holgate ST. 86 94. 🔗 https://doi.org/10.1016/S0031-9406(05)61211-4
- Park (2018). Evaluating test-retest reliability in patient-reported outcome measures for older people: a systematic review. Int J Nurs Stud., 79 58. 🔗 https://doi.org/10.1016/j.ijnurstu.2017.11.003
- Fuhua (2021). A study on the status quo of psychological pain in low-income type 2 diabetic patients based on confirmatory factor analysis. Gen Nurs., 19 2449. 🔗 https://doi.org/10.12104/j.issn.1674-4748.2021.18.001
- Kuczmarski (2021). Healthy behaviors associated with changes in mental and physical strength in Urban African American and white Adults. Nutrients., 13 1824. 🔗 https://doi.org/10.3390/nu13061824
- Lingling (2021). Questionnaire validation factor analysis of factors influencing long-term care needs of disabled elderly people. Med Res Educ., 38 59. 🔗 https://doi.org/10.3969/j.issn.1674-490X.2021.05.009
- Liu (2021). Xu J. Reliability and validity of Healthy Fitness Measurement Scale Version10 (HFMS V10) in Chinese elderly people. BMC Public Health., 21 1019. 🔗 https://doi.org/10.1186/s12889-021-11021-2
- Hatami (2021). Psychometric properties of the Persian version of the Physical Activity Scale for the Elderly (PASE). BMC Geriatr., 21 383. 🔗 https://doi.org/10.1186/s12877-021-02337-0
- Waltz (2016). Measurement in Nursing and HealthResearch. 87. 🔗 https://doi.org/10.1891/9780826170620
Cite this article
Mohammed looti (2026). Healthy Aging Activity Engagement Scale. PSYCHOLOGICAL SCALES. Retrieved from https://scales.arabpsychology.com/s/healthy-aging-activity-engagement-scale/
Mohammed looti. "Healthy Aging Activity Engagement Scale." PSYCHOLOGICAL SCALES, 14 Aug. 2026, https://scales.arabpsychology.com/s/healthy-aging-activity-engagement-scale/.
Mohammed looti. "Healthy Aging Activity Engagement Scale." PSYCHOLOGICAL SCALES, 2026. https://scales.arabpsychology.com/s/healthy-aging-activity-engagement-scale/.
Mohammed looti (2026) 'Healthy Aging Activity Engagement Scale', PSYCHOLOGICAL SCALES. Available at: https://scales.arabpsychology.com/s/healthy-aging-activity-engagement-scale/.
[1] Mohammed looti, "Healthy Aging Activity Engagement Scale," PSYCHOLOGICAL SCALES, vol. X, no. Y, ص Z-Z, August, 2026.
Mohammed looti. Healthy Aging Activity Engagement Scale. PSYCHOLOGICAL SCALES. 2026;vol(issue):pages.