Table of Contents
Abstract
The Health Care Workers' Concerns in infectious outbreaks Scale (HCWCIOS) is a specialized psychometric instrument engineered to quantify the multifaceted anxieties experienced by medical personnel during pandemic events. Developed in response to the profound occupational and psychological toll of the COVID-19 crisis, this tool moves beyond generic stress measures to capture the unique, context-specific worries of frontline staff. By systematically evaluating these concerns, the scale provides a critical metric for healthcare administrators seeking to safeguard their workforce and maintain operational continuity during global health emergencies.
Constructed through a rigorous exploratory sequential mixed-methods design, the HCWCIOS bridges qualitative insights from active healthcare workers with robust quantitative validation. The instrument captures a comprehensive spectrum of occupational distress, ranging from tangible deficits in training to the psychological burden of social stigmatization. For researchers and occupational health professionals, this scale represents a vital advancement in pandemic preparedness, offering a validated framework to identify vulnerable staff cohorts and implement targeted psychological interventions before burnout or absenteeism compromises patient care.
📊 Psychometric Scorecard
36
Multidimensional
0.91
📍 Iran
Authors
Purpose
Historically, research into the psychological impact of pandemics on medical staff relied heavily on ad-hoc or unvalidated questionnaires, limiting the reliability and cross-comparability of findings. The HCWCIOS was developed to address this critical methodological gap by providing a psychometrically sound, standardized measure specifically tailored to the nuances of infectious disease outbreaks.
For clinicians and healthcare administrators, this instrument is invaluable because it disaggregates generalized pandemic stress into actionable domains. By pinpointing exactly what is driving staff anxiety—whether it is a lack of protective equipment, fear of infecting family members, or overwhelming patient loads—leadership can deploy precise, evidence-based support strategies rather than relying on generic wellness initiatives.
Construct
The psychological construct of pandemic-related occupational concern measured by the HCWCIOS is conceptualized as a multidimensional phenomenon encompassing cognitive, environmental, and social domains. Rather than viewing anxiety as a purely internal affective state, this framework recognizes that healthcare worker distress emerges from the interaction between the individual and their high-risk occupational environment.
The construct is operationalized across six distinct dimensions: perceived deficits in institutional readiness, informational gaps regarding the pathogen, cognitive appraisals of personal danger, the deterioration of interpersonal networks due to stigma, the acute burden of clinical duties, and the behavioral consequence of these stressors. Together, these dimensions form a holistic model of occupational vulnerability during biological crises.
Validity
To ensure the instrument accurately captures the intended construct, the developers employed a comprehensive validation protocol starting with a strong qualitative foundation. Face and content validity were meticulously established through expert review and participant feedback, utilizing quantitative metrics to objectively eliminate weak items. The scale achieved an exceptional average Scale-Level Content Validity Index of 0.93, indicating near-unanimous expert agreement on the relevance of the retained items.
Construct validity was subsequently confirmed through exploratory techniques, demonstrating that the theoretical dimensions of pandemic concern mapped cleanly onto distinct statistical factors. This rigorous alignment between theory and statistical output provides strong empirical support that the HCWCIOS measures exactly what it claims to measure.
Reliability
The psychometric stability of the HCWCIOS is robust, demonstrating excellent internal consistency and temporal reliability. When evaluating how well the items within the scale correlate with one another, the overall instrument yielded a Cronbach's alpha of 0.912, which sits well above the conventional threshold for excellent reliability in psychological testing. The individual subscales also performed admirably, with alpha values ranging from 0.735 to 0.864, indicating that each specific domain reliably captures its target facet of concern without excessive redundancy.
Furthermore, the instrument's stability over time was confirmed via test-retest methodology, producing an intra-class correlation coefficient of 0.880. This high degree of temporal stability is particularly crucial for longitudinal research, ensuring that any measured changes in staff concerns over the course of a pandemic reflect true psychological shifts rather than measurement error.
Factor Analysis
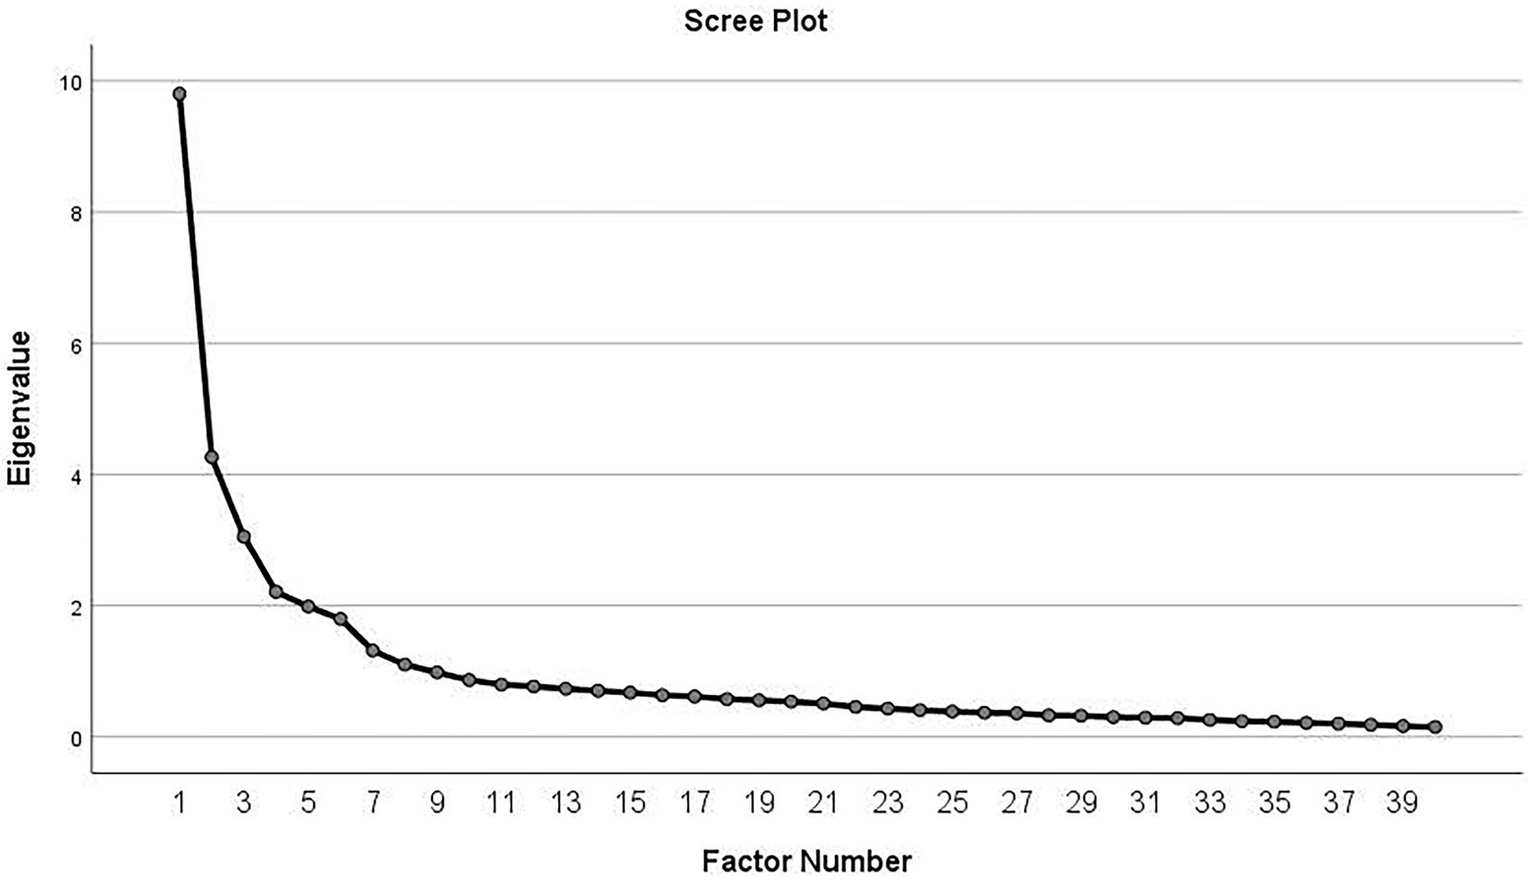
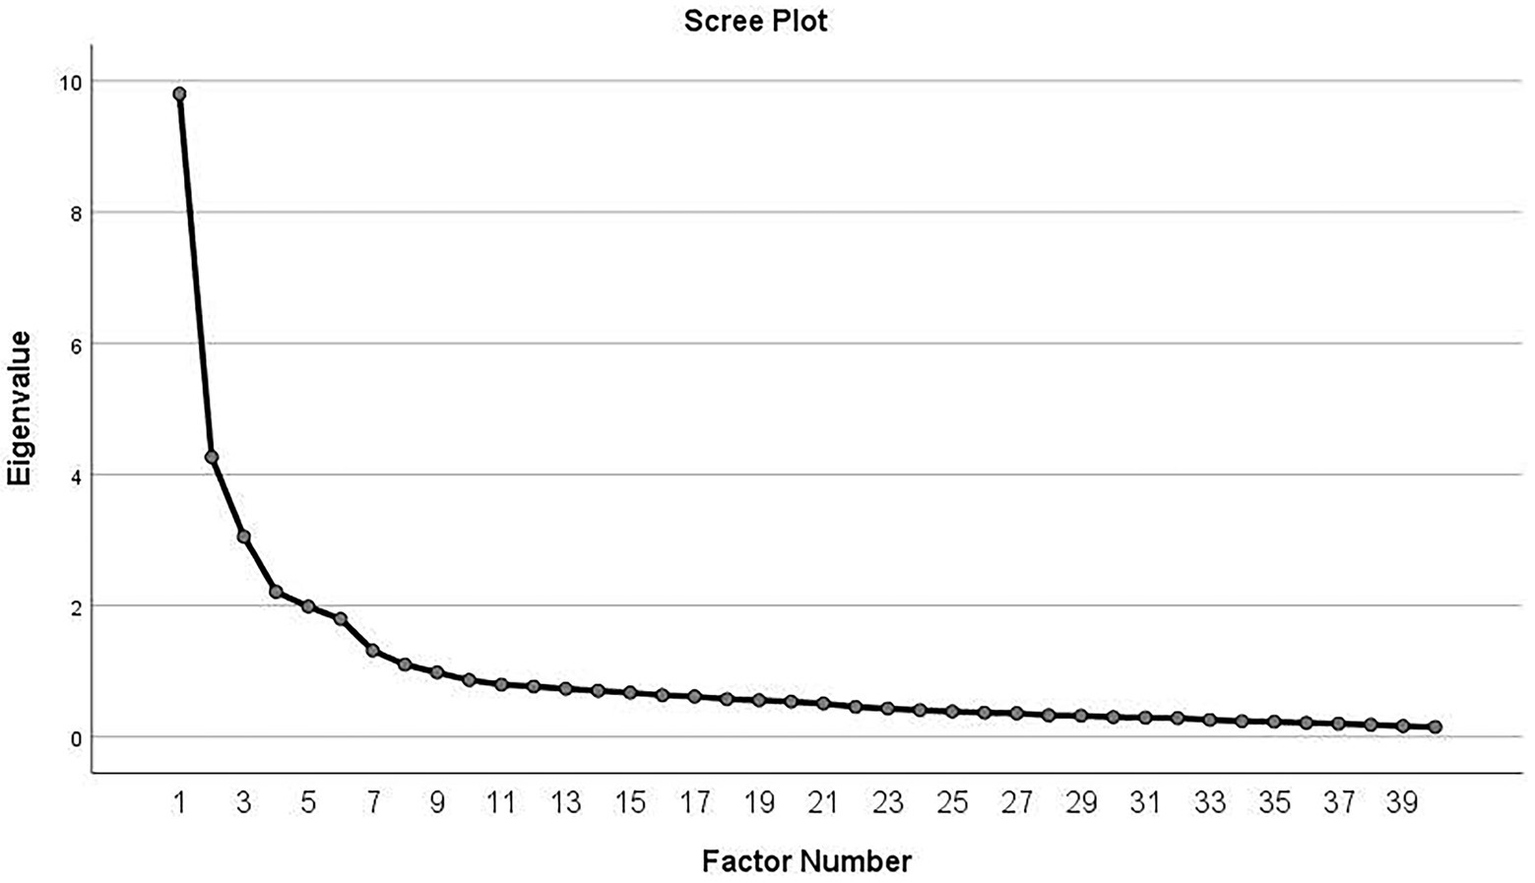
The underlying architecture of the HCWCIOS was delineated using Exploratory Factor Analysis, a statistical technique used to uncover the latent variables driving participants' responses. The dataset proved highly suitable for this approach, as evidenced by a Kaiser-Meyer-Olkin measure of 0.872 and a highly significant Bartlett's test.
Through principal component extraction and Varimax rotation, the analysis distilled the initial item pool into a clean, six-factor structure that collectively accounts for 46.507% of the total variance in healthcare workers' concerns. During this rigorous process, items that failed to load strongly onto a single factor were systematically eliminated, refining the tool from 57 preliminary questions down to a highly optimized 36-item final scale.
Subscales
| Subscale | Items | Description |
|---|---|---|
| Inadequate Preparedness | 8 items | Evaluates concerns regarding the lack of institutional readiness, skills, and equipment to handle the pandemic. |
| Lack of Knowledge | 7 items | Assesses worries stemming from insufficient information, specialized expertise, and understanding of the novel pathogen. |
| Risk Perception | 6 items | Measures the cognitive appraisal of personal danger and the perceived threat of contracting or transmitting the disease. |
| Affected Social Relations | 6 items | Captures the psychological impact of social stigmatization, isolation, and strained interpersonal dynamics due to working in high-risk environments. |
| Work Pressure | 6 items | Quantifies distress related to increased clinical workloads, occupational stress, and the acute demands of patient care during an outbreak. |
| Absenteeism | 3 items | Evaluates the behavioral consequences of pandemic-related stress, specifically the urge or necessity to miss work. |
Instrument
| Test Type | Self-report questionnaire |
| Format | 36 items |
| Language | Persian |
| Population | Healthcare professionals, Nurses |
| Age Group | Adults |
| Administration | Electronic questionnaire |
Figures


Health Care Workers' Concerns in Infectious Outbreaks Scale Items
Items are currently not available
The individual items of this scale are not publicly available. Researchers interested in using this instrument should contact the original authors directly to request the scale materials.
Sample
304 Iranian healthcare workers (mean age = 32.25 years, SD = 7.34). The sample was predominantly female (67.10%), married (60.20%), and held bachelor's degrees (70.40%). Nurses comprised 55.30% of the sample, and 88.10% had direct contact with patients. Participants were recruited via convenient sampling.
Cite This Paper
Sajad Yarahmadi, Mojgan Khademi, Farzad Ebrahimzadeh, Tayebeh Cheraghian, Elham Shahidi Delshad (2022). Health Care Workers' Concerns in infectious outbreaks Scale. Frontiers in psychology. https://doi.org/10.3389/fpsyg.2022.1108835
References
53 references
- Abolfotouh (2017). An assessment of the level of concern among hospital-based health-care workers regarding MERS outbreaks in Saudi Arabia. BMC Infect. Dis., 17 4. 🔗 https://doi.org/10.1186/s12879-016-2096-8
- Alsubaie (2019). Middle East respiratory syndrome coronavirus epidemic impact on healthcare workers’ risk perceptions, work and personal lives. J. Infect. Dev. Ctries., 13 920. 🔗 https://doi.org/10.3855/jidc.11753
- Amakiri (2020). Psychological effect of pandemic COVID-19 on families of health care professionals. Br. J. Psychol. Res., 8 1.
- Arefi (2022). Risk perception in the COVID-19 pandemic; a health promotion approach. J. Educ. Health Promot., 11 118. 🔗 https://doi.org/10.4103/jehp.jehp_1162_21
- Bagcchi (2020). Stigma during the COVID-19 pandemic. Lancet Infect. Dis., 20 782. 🔗 https://doi.org/10.1016/S1473-3099(20)30498-9
- Bandyopadhyay (2020). Infection and mortality of healthcare workers worldwide from COVID-19: a systematic review. BMJ Glob. Health, 5 e003097. 🔗 https://doi.org/10.1136/bmjgh-2020-003097
- Barello (2020). Burnout and somatic symptoms among frontline Healthcare professionals at the peak of the Italian COVID-19 pandemic. Psychiatry Res., 290 113129. 🔗 https://doi.org/10.1016/j.psychres.2020.113129
- Berkhout (2021). Individual- and institutional-level concerns of health care workers in Canada during the COVID-19 pandemic: a qualitative analysis. JAMA Netw. Open, 4 e2118425. 🔗 https://doi.org/10.1001/jamanetworkopen.2021.18425
- Billings (2021). Experiences of frontline healthcare workers and their views about support during COVID-19 and previous pandemics: a systematic review and qualitative meta-synthesis. BMC Health Serv. Res., 21 1. 🔗 https://doi.org/10.1186/s12913-021-06917-z
- Borek (2022). Experiences and concerns of health workers throughout the first year of the COVID-19 pandemic in the UK: a longitudinal qualitative interview study. PLoS One, 17 e0264906. 🔗 https://doi.org/10.1371/journal.pone.0264906
- Bruine De Bruin (2020). Relationships between initial COVID-19 risk perceptions and protective health behaviors: a national survey. Am. J. Prev. Med., 59 157. 🔗 https://doi.org/10.1016/j.amepre.2020.05.001
- Chakravorty (2020). An online survey of Healthcare professionals in the COVID-19 pandemic in the UK. Sushruta J. Health Policy Opin., 13 🔗 https://doi.org/10.38192/13.2.9
- Chaudhary (2020). Concerns, perceived impact, and preparedness of oral healthcare workers in their working environment during COVID-19 pandemic. J. Occup. Health, 62 e12168. 🔗 https://doi.org/10.1002/1348-9585.12168
- Chigwedere (2021). The impact of epidemics and pandemics on the mental health of healthcare workers: a systematic review. Int. J. Environ. Res. Public Health, 18 6695. 🔗 https://doi.org/10.3390/ijerph18136695
- Chua (2021). Nurses’ preparedness, readiness, and anxiety in managing COVID-19 pandemic. Asia Pac. J. Public Health, 33 564. 🔗 https://doi.org/10.1177/10105395211012170
- Cori (2020). Risk perception and COVID-19. 17 3114. 🔗 https://doi.org/10.3390/ijerph17093114
- Cresswell (2011). Designing and Conducting Mixed Methods Research.
- Duffy (2022). What can we learn from the past? Pandemic health care workers’ fears, concerns, and needs: a review. J. Patient Saf., 18 52. 🔗 https://doi.org/10.1097/PTS.0000000000000803
- Ebadi (2017). Principles of scale development in Health Science.
- Fernandez (2020). Implications for COVID-19: a systematic review of Nurses’ experiences of working in acute care hospital settings during a respiratory pandemic. Int. J. Nurs. Stud., 111 103637. 🔗 https://doi.org/10.1016/j.ijnurstu.2020.103637
- Goulia (2010). General hospital staff worries, perceived sufficiency of information and associated psychological distress during the a/H1N1 influenza pandemic. BMC Infect. Dis., 10 1. 🔗 https://doi.org/10.1186/1471-2334-10-322
- Greene (2021). Predictors and rates of PTSD, depression and anxiety in UK frontline health and social care workers during COVID-19. Eur. J. Psychotraumatol., 12 1882781. 🔗 https://doi.org/10.1080/20008198.2021.1882781
- Grove (2012). The Practice of Nursing Research: Appraisal, Synthesis, and Generation of Evidence.
- Heidarijamebozorgi (2021). The prevalence of depression, anxiety, and stress among Nurses during the coronavirus disease 2019: a comparison between Nurses in the frontline and the second line of care delivery. Nurs. Midwifery Stud., 10 188.
- Jalili (2021). Burnout among Healthcare professionals during COVID-19 pandemic: a cross-sectional study. Int. Arch. Occup. Environ. Health, 94 1345. 🔗 https://doi.org/10.1007/s00420-021-01695-x
- Jamebozorgi (2021). Nurses burnout, resilience, and its association with socio-demographic factors during COVID-19 pandemic. Front. Psych., 12 803506. 🔗 https://doi.org/10.3389/fpsyt.2021.803506
- Johnson (2021). Face validity. 1957. 🔗 https://doi.org/10.1007/978-3-319-91280-6_308
- Khademipour (2017). Crowd simulations and determining the critical density point of emergency situations. Disaster Med. Public Health Prep., 11 674. 🔗 https://doi.org/10.1017/dmp.2017.7
- Kinariwala (2020). Concerns and fears of Indian dentists on professional practice during the coronavirus disease 2019 (COVID-19) pandemic. Oral Dis., 27 730. 🔗 https://doi.org/10.1111/odi.13459
- Koh (2005). Risk perception and impact of severe acute respiratory syndrome (SARS) on work and personal lives of healthcare workers in Singapore What can we learn?. Med. Care, 43 676. 🔗 https://doi.org/10.1097/01.mlr.0000167181.36730.cc
- Lai (2020). Factors associated with mental health outcomes among health care workers exposed to coronavirus disease 2019. JAMA Netw. Open, 3 e203976. 🔗 https://doi.org/10.1001/jamanetworkopen.2020.3976
- Lau (2005). SARS-related perceptions in Hong Kong. Emerg. Infect. Dis., 11 417. 🔗 https://doi.org/10.3201/eid1103.040675
- Lawshe (1975). A quantitative approach to content validity. Pers. Psychol., 28 563. 🔗 https://doi.org/10.1111/j.1744-6570.1975.tb01393.x
- Malekshahi Beiranvand (2018). Health care workers challenges during coronavirus outbreak: The qualitative study. RBS, 18 180.
- Molavi-Taleghani (2020). A proactive risk assessment through healthcare failure mode and effect analysis in pediatric surgery department. J. Compr. Pediatr., 11 e56008. 🔗 https://doi.org/10.5812/compreped.56008
- Moseley (2020). Nursing perspectives on their COVID-19 pandemic preparedness. Nurse Pract., 7 7. 🔗 https://doi.org/10.7243/2056-9157-7-3
- Muller (2020). The mental health impact of the COVID-19 pandemic on healthcare workers, and interventions to help them: a rapid systematic review. Psychiatry Res., 293 113441. 🔗 https://doi.org/10.1016/j.psychres.2020.113441
- Pahlevan Sharif (2020). Factor Analysis and Structural Equation Modeling With SPSS and AMOS.
- Polit (2007). Is the CVI an acceptable indicator of content validity? Appraisal and recommendations. Res. Nurs. Health, 30 459. 🔗 https://doi.org/10.1002/nur.20199
- Polit (2016). Measurement and the Measurement of Change: A Primer for the Health Professions.
- Que (2020). Psychological impact of the COVID-19 pandemic on healthcare workers: a cross-sectional study in China. Gen. Psychiatr., 33 e100259. 🔗 https://doi.org/10.1136/gpsych-2020-100259
- Qureshi (2005). Health care workers’ ability and willingness to report to duty during catastrophic disasters. J. Urban Health, 82 378. 🔗 https://doi.org/10.1093/jurban/jti086
- Sadique (2007). Precautionary behavior in response to perceived threat of pandemic influenza. Emerg. Infect. Dis., 13 1307. 🔗 https://doi.org/10.3201/eid1309.070372
- Saggino (1996). Item factor analysis of the Italian version of the death anxiety scale. J. Clin. Psychol., 52 329. 🔗 https://doi.org/10.1002/(SICI)1097-4679(199605)52:3<329::AID-JCLP11>3.0.CO;2-K
- Sahashi (2021). Worries and concerns among healthcare workers during the coronavirus 2019 pandemic: a web-based cross-sectional survey. Humanit. Soc. Sci. Commun., 8 1. 🔗 https://doi.org/10.1057/s41599-021-00716-x
- Seale (2009). “Will they just pack up and leave?”–attitudes and intended behaviour of hospital health care workers during an influenza pandemic. BMC Health Serv. Res., 9 1. 🔗 https://doi.org/10.1186/1472-6963-9-30
- Sheikhbardsiri (2022). Workplace violence against prehospital paramedic personnel (city and road) and factors related to this type of violence in Iran. J. Interpers. Violence, 37 NP11683. 🔗 https://doi.org/10.1177/0886260520967127
- Shiao (2007). Factors predicting Nurses’ consideration of leaving their job during the SARS outbreak. Nurs. Ethics, 14 5. 🔗 https://doi.org/10.1177/0969733007071350
- Sperling (2021). Nurses’ challenges, concerns and unfair requirements during the COVID-19 outbreak. Nurs. Ethics, 28 1096. 🔗 https://doi.org/10.1177/09697330211005175
- Tabachnick (2007). Using Multivariate Statistics.
- Temsah (2020). The psychological impact of COVID-19 pandemic on health care workers in a MERS-CoV endemic country. J. Infect. Public Health, 13 877. 🔗 https://doi.org/10.1016/j.jiph.2020.05.021
- Wong (2008). Concerns, perceived impact and preparedness in an avian influenza pandemic–a comparative study between healthcare workers in primary and tertiary care. Ann. Acad. Med. Singap., 37 96. 🔗 https://doi.org/10.47102/annals-acadmedsg.V37N2p96
- Yusefi (2022). Health human resources challenges during COVID-19 pandemic; evidence of a qualitative study in a developing country. PLos One, 17 e0262887. 🔗 https://doi.org/10.1371/journal.pone.0262887
Cite this article
Mohammed looti (2026). Health Care Workers’ Concerns in Infectious Outbreaks Scale. PSYCHOLOGICAL SCALES. Retrieved from https://scales.arabpsychology.com/s/health-care-workers-concerns-in-infectious-outbreaks-scale/
Mohammed looti. "Health Care Workers’ Concerns in Infectious Outbreaks Scale." PSYCHOLOGICAL SCALES, 14 Aug. 2026, https://scales.arabpsychology.com/s/health-care-workers-concerns-in-infectious-outbreaks-scale/.
Mohammed looti. "Health Care Workers’ Concerns in Infectious Outbreaks Scale." PSYCHOLOGICAL SCALES, 2026. https://scales.arabpsychology.com/s/health-care-workers-concerns-in-infectious-outbreaks-scale/.
Mohammed looti (2026) 'Health Care Workers’ Concerns in Infectious Outbreaks Scale', PSYCHOLOGICAL SCALES. Available at: https://scales.arabpsychology.com/s/health-care-workers-concerns-in-infectious-outbreaks-scale/.
[1] Mohammed looti, "Health Care Workers’ Concerns in Infectious Outbreaks Scale," PSYCHOLOGICAL SCALES, vol. X, no. Y, ص Z-Z, August, 2026.
Mohammed looti. Health Care Workers’ Concerns in Infectious Outbreaks Scale. PSYCHOLOGICAL SCALES. 2026;vol(issue):pages.